An anion gap calculator is a practical medical calculator designed to assist interpret an electrolyte panel and spot important patterns in serum chemistry. By reviewing serum sodium, serum chloride, and serum bicarbonate, it can reveal clues about metabolic acidosis, electrolyte imbalance, and other forms of acid-base disorder. Although the calculation is basic, the clinical meaning depends on the broader blood chemistry, the patient’s symptoms, and key modifiers such as albumin.
In the right context, the anion gap is more than a number. It is a screening tool that improves clinical interpretation, highlights unmeasured anions, and helps narrow the diagnostic workflow. It also helps clinicians see when a result may reflect lab variability, a corrected value problem, or a true clue to serious disease.
What Is the Anion Gap?
The anion gap is a calculated value based on an electrolyte panel that approximates the difference between routinely measured cations and anions in the blood. It is not directly measured; instead, it indicates the equilibrium between positively charged and negatively charged substances in the serum electrolytes. In clinical practice, it is mainly used to assess metabolic acidosis and support acid-base interpretation.
Because routine testing does not measure every charged particle in the blood, the anion gap serves as a clue to the presence of unmeasured anions. These may include lactate, ketones, toxins, or other acids. A higher-than-expected result often points toward high anion gap metabolic acidosis, while a expected or low value may suggest normal anion gap metabolic acidosis, a measurement issue, or another process affecting the serum balance.
In simple terms, the anion gap helps answer a clinical question: is there an anion deficit or an excess of unmeasured acids in the bloodstream? That makes it a helpful starting point for understanding the patient’s lab results and deciding what to investigate next.
How to Work Out the Anion Gap
This calculation uses three values from the electrolyte panel: sodium, chloride, and bicarbonate. The classic anion gap formula uses these measured concentrations to estimate the gap between positive and negative ions. Because the values are part of routine serum chemistry, the calculation can be performed rapidly at the bedside or within an anion gap calculator.
Knowing the formula is important because the result depends on the concentration of each component. Small shifts in serum sodium, serum chloride, or serum bicarbonate can change the number and alter the clinical interpretation. A calculator helps with speed, but the user still needs to understand the underlying pathophysiology.
Classic Anion Gap Formula
The classic calculation is:
Na minus Cl minus HCO3with Na meaning sodium, Cl is chloride, and HCO3 is bicarbonate. The calculation steps are easy:
- Enter the measured serum sodium. Next subtract the measured serum chloride. Then subtract the measured serum bicarbonate.
This value is then compared with a reference range, which can vary depending on the laboratory method and analyzer. In many settings, the reference interval is roughly in the single digits to low teens, but always rely on the laboratory-specific reference range rather than a fixed universal number.
For instance, if sodium is 140, chloride is 104, and bicarbonate is 24, the anion gap is 12. That result may fall within the expected range, but interpretation depends on whether the patient also has metabolic acidosis, altered albumin, or another abnormality.
Albumin-Corrected Anion Gap
Albumin is a major unmeasured anion, so low albumin can make the gap appear falsely normal or low. This is especially important in hypoalbuminemia, where the apparent result may downplay the true burden of acids. In those cases, the corrected anion gap is more informative than the raw value.
The adjustment accounts for the impact of lower protein binding and fewer negatively charged molecules in the serum. If albumin is low, the body has fewer baseline unmeasured anions, which can mask a clinically important acid load. That is why the albumin-adjusted result is often a more accurate corrected value for clinical interpretation.
In clinical practice, a patient with hypoalbuminemia may have a “normal” anion gap that still hides high anion gap metabolic acidosis. A calculator that applies albumin correction can increase the diagnostic yield and reduce missed acid-base disorder patterns.
How to Interpret Elevated, Average, and Reduced Anion Gap Findings
Assessment depends on the overall pattern, not just the value. A elevated anion gap typically points to extra unmeasured acids. A typical anion gap can still be seen with metabolic acidosis, especially when bicarbonate loss is compensated by increased chloride. A reduced anion gap is less common but can be a useful clue or an artifact.
When using an anion gap calculator, first by asking whether the result fits the patient’s symptoms and other lab results. The same number may represent very different things depending on pH, bicarbonate, albumin, and whether there is a concurrent respiratory disorder. This is why acid-base interpretation is always a clinical task, not a purely mathematical one.
A high anion gap usually suggests metabolic acidosis with a high anion gap. A standard anion gap with acidosis often points toward metabolic acidosis with a normal anion gap and may be associated with hyperchloremia. A reduced anion gap often brings up laboratory error, low albumin, or uncommon causes such as excess unmeasured cations.
Common Causes of Elevated Anion Gap
Elevated results often reflect greater acid generation, reduced acid removal, or consumption of substances that contribute unmeasured anions. The leading diagnostic categories include lactic acidosis, ketoacidosis, renal failure, and toxic ingestions. Recognizing these patterns helps turn a number into a practical diagnostic clue.
Lactic acidosis occurs when tissue hypoperfusion, sepsis, hypoxia, or mitochondrial dysfunction leads to lactate accumulation. This is a typical cause of high anion gap metabolic acidosis. Ketoacidosis may arise in diabetes, alcohol use, or prolonged fasting, and the building ketones increase the anion gap.
Renal failure can https://anion-gap-help585.inkharbory.com/posts/which-drugs-can-lead-to-a-high-anion-gap cause retained acids and reduced excretion of unmeasured anions. In advanced kidney dysfunction, the gap may climb over time as acid handling worsens. This is why kidney function should be reviewed alongside the electrolyte panel, especially when the clinical interpretation suggests a progressive metabolic problem.
Toxic ingestions are another key category. Toxic alcohol ingestion can produce a substantial gap by generating acidic metabolites, and salicylate poisoning can create mixed acid-base patterns with an elevated gap. These cases often require a deliberate diagnostic workflow because the acid-base picture may be complex and time-sensitive.
When the Anion Gap Is Normal
A normal finding does not eliminate acid-base disease. Indeed, normal anion gap metabolic acidosis is widely seen and often associated with bicarbonate loss with compensatory chloride retention. This pattern is frequently called hyperchloremic metabolic acidosis because chloride rises as bicarbonate falls, keeping the gap in the reference interval.
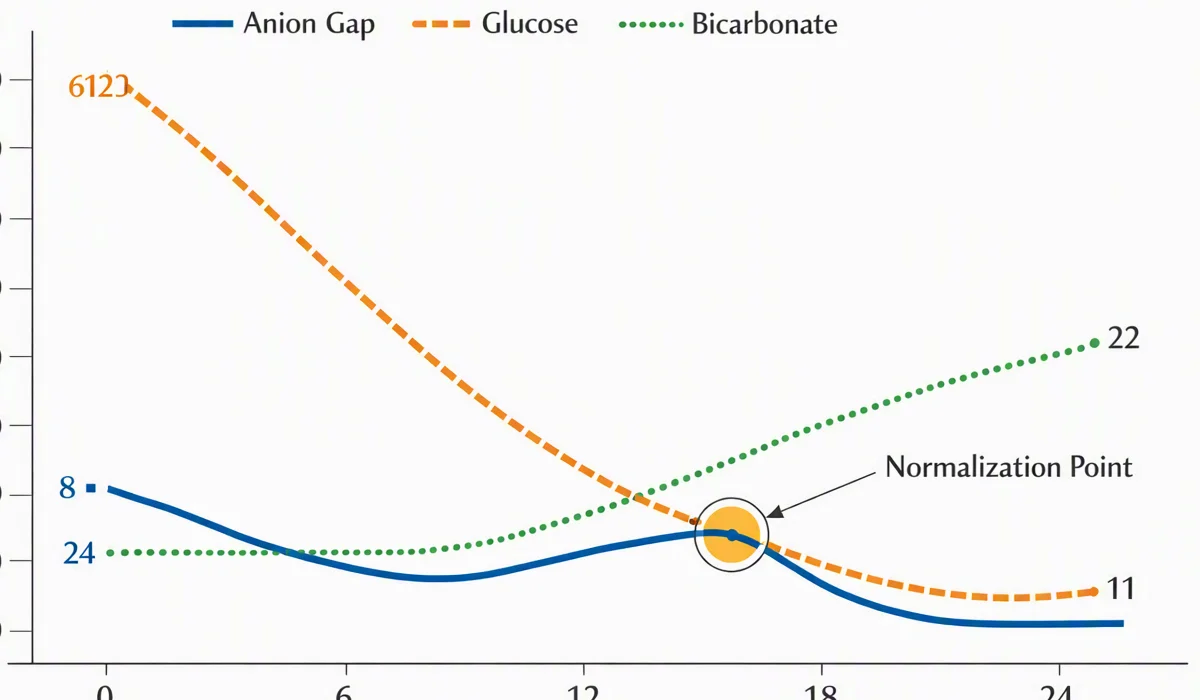
A normal gap can be seen in diarrhea, renal tubular acidosis, and other bicarbonate-losing states. It can also occur during recovery from a previously elevated gap, when unmeasured anions are being cleared and chloride has risen in compensation. Because of this, the pattern over time matters as much as the single result.
A low anion gap is uncommon but should not be dismissed. Laboratory error is one of the first things to consider, because small measurement issues can strongly affect the calculation. A low result can also occur with paraproteinemia, where abnormal proteins act as cations or alter the balance of measured ions. In other situations, lithium may function as an unmeasured cation and lower the gap.
When chloride is unexpectedly high, look for hyperchloremia, which may indicate a true normal-gap acidosis or a compensatory change. In each case, the finding should be interpreted in the context of the overall acid-base disorder, the patient’s symptoms, and the rest of the electrolyte panel.
Stepwise Workflow for Electrolyte Panel Interpretation
A systematic approach strengthens electrolyte panel interpretation and decreases missed diagnoses. The aim is not only to determine the value, but to put it within a larger diagnostic workflow.
- Step 1: Check sodium, chloride, and bicarbonate on the electrolyte panel. Step 2: Determine the anion gap using the anion gap formula or an anion gap calculator. Step 3: Check the result with the lab’s reference range. Step 4: Check albumin and assess a corrected anion gap if hypoalbuminemia is present. Step 5: Examine the ABG if available to evaluate pH, respiratory compensation, and mixed disorders. Step 6: If the gap is elevated, evaluate lactate, ketones, kidney function, and toxic exposures. Step 7: Apply the delta gap when a mixed disorder may be present.
The ABG adds crucial context because it clarifies whether there is acidemia, alkalemia, or compensation that is masking the primary problem. The delta gap is important when an elevated anion gap does not fully explain the bicarbonate change, suggesting a mixed acid-base disorder. This systematic process improves acid-base interpretation and supports more accurate clinical decisions.
Always interpret the numbers with the patient’s symptoms, medications, kidney function, and overall presentation. The best results come from combining calculator output with clinical context.
Drawbacks of the Anion Gap Calculator
An anion gap calculator is valuable, but it is not conclusive. One major constraint is the albumin effect, which can conceal clinically important acid accumulation when albumin is low. Without compensation, the calculated result may downplay the severity of the disorder.
Another limitation is the presence of unmeasured cations such as lithium or other unusual positively charged substances. These can lower the gap and make interpretation harder. In addition, measurement variability between analyzers can shift the result enough to move it across the reference interval, especially when the number is borderline.
It is also important to remember that the gap is a indicator, not a diagnosis. It does not tell you the exact cause of metabolic acidosis, and it does not replace broader assessment of blood gases, renal function, lactate, ketones, and medication or toxin exposure. Used well, it improves the diagnostic picture; used alone, it can mislead.
In other words, the calculator is most valuable as part of a full interpretation guide. It helps clarify the problem, but the final answer comes from synthesis.
Frequently Asked Questions
What is the normal range for the anion gap?
The anion gap normal range depends on the laboratory method and analyzer, so the best number to use is the lab-specific reference range. In many settings, the range is in the single digits to low teens. Always interpret the result in the context of the local serum chemistry method and the patient’s clinical picture.
How does albumin affect the anion gap?
Albumin is a major unmeasured anion, so low albumin can make the anion gap appear falsely low or normal. This is why hypoalbuminemia can hide important acid-base abnormalities. A corrected anion gap helps adjust for that effect and improves clinical interpretation.
What does a high anion gap mean on an electrolyte panel?
A high anion gap usually means there are extra unmeasured anions in the blood, often due to high anion gap metabolic acidosis. Typical causes include lactic acidosis, ketoacidosis, renal failure, toxic alcohol ingestion, and salicylate poisoning. The result is a diagnostic clue, not a conclusive diagnosis.
Can a normal anion gap still indicate metabolic acidosis?
Yes. A normal result can still be compatible with normal anion gap metabolic acidosis, especially when bicarbonate loss is balanced by rising chloride. This pattern is often called hyperchloremic metabolic acidosis. That is why the full electrolyte panel, ABG, and clinical context are so important.
Why might an anion gap calculator give a low result?
A low result may reflect laboratory error, low albumin, paraproteinemia, or the presence of lithium or other unmeasured cations. It can also occur because of normal measurement variability around the reference interval. If the number does not fit the clinical picture, repeat testing and broader acid-base interpretation are important.