An Anion Gap Calculator is a practical tool for rapid lab evaluation, helping you read electrolyte patterns and identify an acid-base abnormality that may need care. In regular screening, the anion gap is especially helpful because it turns a typical electrolyte panel into a more meaningful clinical clue. By looking at sodium, chloride, and bicarbonate together, you can check acid-base balance and detect possible metabolic abnormality sooner.
This calculation is not meant to take the place of clinical judgment. Rather than that, it helps with interpretation of lab values in the right clinical context. For many patients, especially during regular review of a basic metabolic panel or comprehensive metabolic panel, the anion gap provides a fast way to sort abnormal findings and determine whether follow-up is needed.
What the anion gap measures in routine metabolic analysis
The anion gap is a computed value based on standard electrolytes measured in standard testing. It captures the balance between positive and negatively charged ions in the blood, using the main lab measurements most clinicians already review. The core components are sodium, chloride, and bicarbonate.
In basic terms, the anion gap can estimate whether there are unmeasured acids or other charged particles influencing the blood chemistry. That is why it can serve as a diagnostic clue during clinical review. A normal result does not rule out every problem, but it can help focus the evaluation when a patient has symptoms or abnormal lab values.
The calculation is often used as part of an electrolyte panel to support screening for metabolic acidosis. It is not a standalone diagnosis. Instead, it provides another layer to the overall assessment of acid-base balance, especially when electrolyte trends change over time.
A useful way to think about the anion gap is that it helps show whether the body is “missing” measured negative ions or whether extra acids are present. That makes it useful for routine review, follow-up, and quick evaluation of abnormal chemistry results.
How to operate an anion gap calculator step by step
An Anion Gap Calculator is simple to use when you know the right calculator inputs. Most tools need the values for sodium, chloride, and bicarbonate. Some also allow albumin entry so the result can be modified for albumin correction.
The basic anion gap formula is typically: This standard formula is generally:
Anion gap = sodium - (chloride + bicarbonate)
For the calculation step by step:
- Find the patient’s electrolyte values on the lab report. Enter sodium, chloride, and bicarbonate into the calculator. Examine the calculated anion gap. Match the result with the lab’s reference range or reference interval. If albumin is low, consider whether an albumin correction is needed.
When using the calculator, be mindful of units and lab method. Slight changes in reporting can affect the final measurement. For that reason, the result should always be interpreted with the patient’s overall picture, not in isolation.
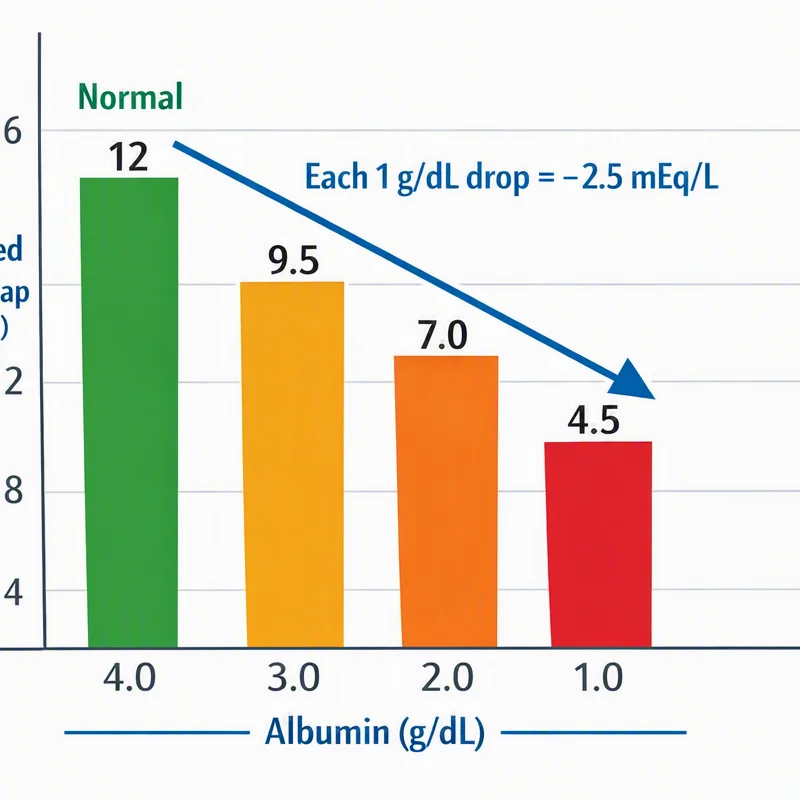
If albumin is included, the calculator may produce an adjusted result. This is especially important because low albumin can mask an elevated anion gap. A quick adjusted calculation can enhance detection during routine review and help reveal a more accurate metabolic pattern.
Typical, elevated, and low anion gap values
A normal anion gap generally implies that the measured electrolytes are in a stable distribution, though this does not guarantee that everything is normal. The expected reference range may vary from one laboratory to another because of laboratory variation in methods and documentation.
A high anion gap metabolic acidosis is the main abnormal finding many clinicians watch for. It indicates that unmeasured acids are accumulating, which can be an serious sign of a metabolic problem needing follow-up. This is one of the most important reasons the anion gap is included in routine lab review.

A low anion gap is uncommon but still relevant. It may indicate lab artifact, low albumin, or other changes affecting ion balance. Because the calculation depends on measured electrolytes, a low value should lead to a careful check for reporting issues and wider clinical interpretation.
It is important to note that laboratory variation can affect whether a value is considered acceptable, mildly abnormal, or clearly abnormal. One lab’s threshold may differ slightly from another’s. That is why using the local reference range matters more than relying on a single universal number.
In everyday practice, the main value of the anion gap is recognizing patterns. A normal value may offer reassurance in some settings, while a high value may point toward a more urgent acid-base disorder. A low value may be a clue to recheck the sample, consider albumin, or review the full chemistry profile.
Typical causes of an abnormal anion gap
When the anion gap is abnormal, the best next step is to consider patterns rather than isolated numbers. In routine review, a number of common conditions can explain an elevated or reduced result. The clinical question is whether the pattern fits the patient’s symptoms, history, and other lab values.
Lactic acidosis is a classic cause of elevated anion gap. When lactate builds up, it contributes to metabolic acidosis and shifts the electrolyte relationship. This is often seen in situations involving poor tissue oxygen delivery, severe illness, or other stress states.
Ketoacidosis is another important cause. In this setting, ketone bodies increase acid load and push the anion gap higher. This pattern can appear in uncontrolled diabetes, prolonged fasting, or other metabolic states where the body burns fat for fuel.
Renal failure can also produce a high anion gap because the kidneys are less able to remove acid effectively. As acid retention increases, the calculation may reflect a broader metabolic disturbance. This makes the anion gap a helpful quick-check marker during chemistry review.
Hypoalbuminemia is a common explanation for a low or misleading result. Since albumin is a major negatively charged protein, a drop in serum albumin can lower the measured gap. This is why albumin should always be part of the interpretation when the result seems unexpected.
Other causes can include medications, toxin exposure, or shifts in the way ions move across compartments. A chloride shift may occur as the body tries to maintain electrical neutrality, changing the relationship between measured electrolytes. Even when the cause is not obvious, the anion gap can still direct the next stage in evaluation.
Correcting the anion gap for albumin
Because albumin contributes significantly to the body’s unmeasured anions, albumin correction is often necessary for a better interpretation. This is especially true when the patient has low serum albumin. Without adjustment, the anion gap may appear normal even when an acid–base problem is present.
The concept behind the correction is straightforward: if albumin is reduced, the measured anion gap may be falsely decreased than expected. An adjusted anion gap corrects for that change and gives a better estimate for clinical interpretation. This can improve assessment in everyday lab review, especially when the numbers do not seem to match the patient’s condition.
Albumin matters because of protein binding and its role as an unmeasured anion. When serum albumin falls, the balance of measured ions changes. The correction helps https://anion-gap-calculation.com/reference/normal-ranges.html restore context to the calculation and improves the quality of the clinical interpretation.
For practical use, albumin correction is most helpful when there is marked hypoalbuminemia or when an otherwise suspicious lab pattern is not explained by the unadjusted result. In those cases, an adjusted calculation may reveal occult metabolic acidosis or support a clearer threshold for concern.
Even when a calculator performs the correction on its own, it remains important to understand what the adjustment means. The corrected value is not a distinct diagnosis. It is a better measurement for judging the real acid-base pattern in context.
How anion gap calculation integrates into regular laboratory review
The anion gap is most helpful when it is part of a broader review of the basic metabolic panel or comprehensive metabolic panel. Such panels provide the raw data that make the calculation possible. In routine lab review, the anion gap helps turn a standard chemistry set into a more meaningful snapshot of acid-base status.
Clinicians often use the result to check for hidden problems, verify that an abnormal electrolyte pattern makes sense, or decide whether further assessment is needed. That is why the anion gap is valuable not just for emergencies, but also for routine review and follow-up. It provides context for the overall clinical interpretation of lab values.
For example, if bicarbonate is low and sodium and chloride are changing in a predictable way, the anion gap can help show whether the pattern fits a high-gap process or a normal-gap process. That distinction matters because it changes the direction of the evaluation.
The anion gap is also useful during trend review. A single number can be informative, but comparing results over time often gives a more complete picture of whether a metabolic issue is improving, stable, or worsening. This is one reason the calculation remains a core part of routine chemistry assessment.
In practical terms, the best use of the anion gap is to support effective decision-making. It can highlight abnormal findings that deserve attention, but it should always be reviewed with the full electrolyte panel, symptoms, and clinical context.
What to do after checking the anion gap
After using the calculator, the next step is not simply to label the result as within range or abnormal. Good interpretation starts with asking whether the value aligns with the rest of the labs and the patient’s clinical picture. If not, you may need further data before making a decision.
Retesting may be appropriate when a result is unexpected or inconsistent with the clinical picture. This may help identify specimen issues, testing variability, or short-term changes. Because testing variation may affect the result, a repeat measurement may determine whether the abnormality is real.
An arterial blood gas test can assist when the acid-base picture is uncertain or more severe assessment is needed. A venous blood gas may also be useful in many cases and can provide additional detail without requiring arterial sampling. Either test can aid deeper assessment of the acid-base balance.
Most importantly, use clinical assessment. Anion gap is just one of several measurements, and it should match the patient’s symptoms, medical history, and other observations. If the result suggests acidosis or a different important metabolic issue, the follow-up should be driven by the full clinical picture.
When the result is abnormal, the next step may include checking medications, hydration status, kidney function, glucose, lactate, or ketones. If the result looks normal but concern remains, determine whether albumin adjustment or repeat evaluation is needed. In short, the calculator helps with initial screening, but interpretation is what turns the number into action.
Frequently asked questions about anion gap results
What is anion gap calculator used for?
An Anion Gap Calculator is used to easily compute the anion gap from standard lab values and aid interpretation of electrolyte results. It assists with screening for metabolic acidosis, assessing acid-base balance, and recognizing patterns that may need follow-up in regular review.
What is a standard anion gap range?
The reference interval for a typical anion gap is determined by the lab and method used. That means there is never one universal number. Always compare the result to the lab-specific reference range listed by the lab and take into account testing variation when reviewing the result.
Why do you modify the anion gap for albumin?
You use albumin correction because low serum albumin can make the anion gap look reduced than it truly is. Since albumin contributes to the body’s negative charge through protein attachment, an albumin-adjusted anion gap can offer a more precise measurement and improve clinical interpretation.
What causes a elevated anion gap?
A elevated anion gap is commonly associated with lactic acid buildup, ketosis-related acidosis, and kidney failure. These conditions raise unmeasured acids and often lead to elevated anion gap metabolic acidosis. The result should always be reviewed with the full clinical context and other lab values.
Can a standard anion gap still mean a problem is present?
Yes. A standard result does not rule out all disease. Some patients may have normal anion gap metabolic acidosis, or the abnormality may be masked by reduced albumin. That is why the anion gap should be considered alongside the rest of the BMP, the comprehensive metabolic panel, and the overall clinical interpretation.