How the Anion Gap Evaluates
The anion gap is a useful way to estimate acid-base balance from common electrolytes reported in a standard lab test. It may reveal whether there are hidden ions in the blood that may point to an acid-base disorder, especially metabolic acidosis. An Anion Gap Calculator relies on serum values such as serum sodium, serum chloride, and serum bicarbonate to make a quick calculation and support interpretation of the result.
The basic idea of the anion gap is simple: sodium is the main measured positive charge, while chloride and bicarbonate are the main measured negative charges. The balance between them provides a clinical clue about the body’s acid-base status. A elevated gap can suggest the presence of unmeasured acids, while a reduced result may reflect shifts in albumin, chloride, or other factors.
In clinical practice, the anion gap is not used alone. It is part of a broader evaluation that includes symptoms, the complete electrolyte panel, kidney function, and sometimes a blood gas. Even so, it remains a rapid screening tool because it can indicate a likely cause of an abnormal result and support further assessment.
How to Work Out Anion Gap with Serum Chloride
The standard approach to determine the anion gap is to use serum sodium, serum chloride, and serum bicarbonate. This basic equation relies on the lab measurement of these three serum values:
Anion gap = Serum sodium − (Serum chloride + Serum bicarbonate)
As an example, if serum sodium is 140 mEq/L, serum chloride is 102 mEq/L, and serum bicarbonate is 24 mEq/L, the calculation is 140 − (102 + 24) = 14 mEq/L. This value can then be compared with the laboratory’s reference range and interpreted in context.
Serum chloride matters because it is one of the two main values subtracted from sodium. A increased chloride level lowers the calculated gap, while https://anion-gap-reader276.publishlane.com/posts/anion-gap-calculator-for-metabolic-workup-interpretation a reduced chloride level raises it. That means the same sodium and bicarbonate values can produce a very different result depending on chloride. For this reason a careful measurement of chloride is essential for precise interpretation.
The calculator can also be used as a supportive diagnostic tool when evaluating possible metabolic acidosis or other electrolyte-related concerns. If the number is outside the expected normal range, the next step is to consider the clinical picture, the pattern of other electrolytes, and whether repeat testing is needed.
Anion Gap Equation and Frequent Variants
The standard anion gap formula is valuable in many clinical contexts, but there are frequent variations that can change the result. Some labs include potassium in the formula:
Anion gap = Serum sodium + Potassium − (Serum chloride + Serum bicarbonate)
As potassium is generally present in a much smaller level than sodium, many providers omit it for simplicity. Even so, knowing the variation matters because it can modestly change the interpretation of a borderline result.
A second key adjustment is albumin correction. Albumin is a anionic protein that helps determine the normal anion gap. When albumin is low, the measured gap may appear incorrectly normal or low even if there is an underlying acid-base disorder. In that case, a corrected calculation can deliver a more reliable assessment.
A typical correction formula is applied to account for reduced albumin. While formulas may vary by institution, the core idea is the same: lower albumin means the expected anion gap should be adjusted upward. This correction formula is especially important in hospitalized patients, where albumin is often abnormal and the uncorrected number may downplay the severity of an acid-base disorder.
Recognizing these variations improves medical relevance. The calculation is only the starting point; interpretation depends on whether the lab uses potassium, whether albumin correction is applied, and whether the measured values match the broader evaluation.
Understanding a Elevated, Average, or Decreased Anion Gap
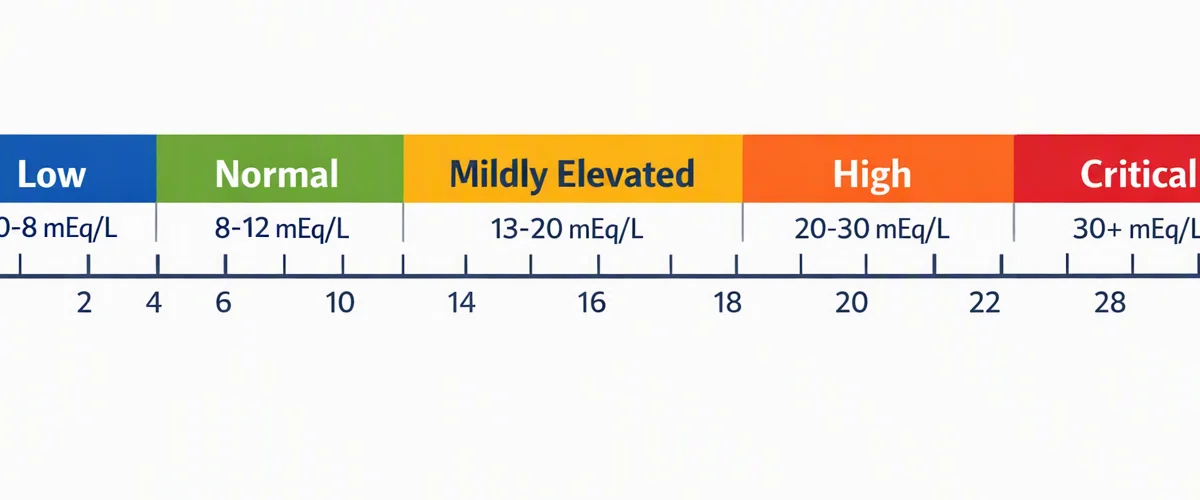
A elevated, average, or decreased result every one leads in a separate pattern. The meaning relies on the normal range used by the lab and the patient’s overall clinical picture.
High anion gap metabolic acidosis implies that more acids are present in the blood in addition to the commonly measured electrolytes. This is often a sign to a more serious underlying cause of metabolic acidosis, and it usually requires prompt assessment.
A normal anion gap doesn’t necessarily mean everything is fine. In some cases, a person can still have normal anion gap metabolic acidosis, also called hyperchloremic metabolic acidosis. In that situation, bicarbonate is depleted or chloride rises in a way that keeps the calculated gap within the normal range.
A low anion gap is unusual, but it can be medically important. It may be related to low albumin, laboratory differences, excess unmeasured cations, or increased chloride relative to sodium. Because low values are unusual, they need a careful check of the lab test and the clinical context.
In practical use, the result should be read as an assessment tool rather than a final diagnosis. The calculation helps determine whether the acid-base status is likely to reflect too much acid, chloride loss, bicarbonate loss, or another electrolyte pattern.
Frequent Causes of Atypical Anion Gap Results
A variety of conditions can cause an unexpected result. One of the most recognized causes of increased anion gap metabolic acidosis are conditions that add to unmeasured acids in the blood.
Lactate buildup is a common cause. It occurs when lactate rises faster than the body can clear it. This may happen in settings of reduced oxygen delivery, shock, severe illness, or impaired metabolism. Because lactate is not directly included in the formula, it increases the anion gap indirectly.
Ketoacidosis is another classic cause. When ketones increase, they act as unmeasured acids and widen the gap. This can occur in diabetes, prolonged fasting, alcohol-related states, or other conditions associated with increased ketone production. A clinician may review the lab pattern with glucose, ketones, and symptoms to support the diagnosis.
Kidney failure can also widen the gap because failing kidneys do not clear acid well. As acids accumulate, bicarbonate drops and the calculated difference may expand. In this setting, the anion gap becomes part of the assessment of kidney-related metabolic acidosis.
Additional abnormal results may indicate mixed processes. For example, a person can have both an elevated lactate and a chloride-related shift, which makes the interpretation more complex. That is why the anion gap should be used as a supportive and supportive measure, not as a standalone diagnosis.

When Serum Chloride Shifts Result Interpretation
Serum chloride serves a major role in how the result is understood. Since chloride is directly subtracted in the formula, even a slight change can alter the final number. This is one reason serum chloride is so important in the Anion Gap Calculator.
Hyperchloremia can decrease the anion gap by raising the negative side of the equation. This may happen when chloride rises to compensate for bicarbonate loss, especially in normal anion gap metabolic acidosis. In that situation, the chloride increase can make the result look less striking than the underlying acid-base disorder actually is.
Hypochloremia can have the opposite effect by raising the calculated gap. When chloride is low, the formula may show a higher value even if the main issue is not excess acid. That is why chloride must be interpreted alongside sodium and bicarbonate rather than in isolation.
A chloride shift can also shape interpretation. If the body retains or loses chloride in response to fluid changes, kidney handling, or acid-base compensation, the resulting pattern can hide or magnify the underlying disorder. Recognizing this shift helps avoid misreading an abnormal result.
In short, serum chloride is not just a number in the formula. It is often the critical clue that explains why the calculation is increased, normal, or low.
How to Operate the Calculator Step by Step
Using an anion gap calculator is simple if you begin with the proper lab results. The process works well when all input values come from the same electrolyte panel and are measured at the same time.
- Input the serum sodium value from the lab results. Input the serum chloride value. Input the serum bicarbonate value. When the calculator permits it, add potassium for the alternate formula. See whether albumin correction is needed before interpreting the result.
After the values are entered, the calculator performs the calculation and compares the answer with the expected reference range. If the value falls outside the range, the result is flagged as an abnormal result and should be assessed in the context of the patient’s symptoms and other measurements.
A helpful workflow is to think of the calculator as a first-pass screening step. It assists identify whether the acid-base disorder is likely to involve unmeasured acids, chloride changes, or bicarbonate loss. After that, the interpretation should be verified with related lab findings and the overall clinical picture.
Limitations and Clinical Considerations
Although the anion gap is clinically useful, it has notable limitations. One important concern is albumin level. Since albumin contributes to the normal gap, low albumin can conceal a clinically important problem. When albumin is not adjusted for, a serious acid-base disorder may be missed.
The blood gas can offer important information, especially when the serum bicarbonate is abnormal or the diagnosis is unclear. The blood gas helps confirm whether there is true acidemia or alkalemia and can provide a fuller assessment of ventilation and buffering.
The biggest limitation, however, is that the number must be interpreted in clinical context. The same lab pattern can mean very different things depending on symptoms, medication use, kidney function, fluid status, and whether the patient has a known acid-base disorder. As an example, a borderline elevated gap in a person with vomiting is not interpreted the same way as the same result in someone with shock or renal failure.
Other important considerations are lab variation, differences in reference range between institutions, and the possibility of mixed disorders. A single calculation is useful, but it is not a final diagnosis. The best evaluation combines the anion gap, albumin, chloride, bicarbonate, and other serum values with the broader clinical picture.
FAQs
What is considered a normal anion gap range?
The anion gap normal range depends on the laboratory and whether potassium is included in the formula. Many labs consider a value in the low to mid-teens to be normal, but the exact reference range should always be taken from the reporting lab. Because methods differ, comparing the result to the correct reference range is more reliable than using a single universal cutoff.
How do you calculate anion gap using serum chloride?
The formula is: serum sodium minus the sum of serum chloride and serum bicarbonate. In other words, Anion gap = Sodium − (Chloride + Bicarbonate). This calculation uses serum chloride directly, so changes in chloride can significantly affect the final answer.
Why is albumin correction essential in anion gap interpretation?
Albumin correction is important because albumin is an important unmeasured anion. If the albumin level is low, the anion gap may seem unchanged or smaller even when an underlying acid-base disorder is present. Accounting for albumin improves the accuracy of the assessment and helps detect a hidden abnormal result.
What does a high anion gap often mean?
A high result usually indicates high anion gap metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, and renal failure. These conditions increase unmeasured acids in the blood, which raises the gap and indicates the need for further evaluation.
Could a normal anion gap still indicate metabolic acidosis?
Yes. A normal anion gap can still occur in normal anion gap metabolic acidosis. In that situation, bicarbonate is often lost and chloride rises to keep the gap within the reference range. This is why serum chloride, bicarbonate, and the overall clinical context play such an important role in interpretation.