How the anion gap measures
The anion gap is a useful way to look at the balance of electrolytes in the blood and to assess acid-base balance. It is not a direct reading of a single substance. Instead, it is a derived value that reflects the difference between positive and negative particles in the bloodstream. Clinicians often use it as a clue when investigating metabolic acidosis and other acid-base disorder patterns.
In practical terms, the anion gap helps detect whether there may be unmeasured acids or other abnormal substances affecting serum levels. Because it is derived from common lab values, it is a valuable diagnostic tool when reviewing blood test results. The result can point toward an electrolyte imbalance or another metabolic disorder that needs more workup.
Although the number itself is simple, its clinical significance depends on the whole picture. A mildly abnormal result may be less concerning than a dramatic change with symptoms. That is why an anion gap should always be considered alongside the patient’s condition, the reference range, and the rest of the chemistry results.
How exactly an anion gap calculator functions
An Anion Gap Calculator relies on basic lab values to calculate anion gap quickly and uniformly. Typical calculators ask for sodium, chloride, and bicarbonate, which are usually included on a standard chemistry report. By entering those values, the calculator performs the anion gap formula and returns a result that can be checked with the expected reference range.
The reason this works is that sodium is the main measured cation, while chloride and bicarbonate make up major measured anions. The difference between them gives a useful estimate of unmeasured ions in the blood. When the gap is widened, clinicians may consider acids that are not directly measured on a routine electrolyte panel.
An Anion Gap Calculator is especially helpful when reviewing complex blood test results or checking whether an abnormal value aligns with the overall pattern. It can support more rapid interpretation, but it does not replace clinical judgment. The same number can have different meaning depending on the patient, the lab method, and the other lab values present.
Anion gap calculation and example calculations
The most common anion gap formula is:
Anion gap = serum sodium − (serum chloride + serum bicarbonate)
This formula uses serum sodium, serum chloride, and serum bicarbonate from a routine chemistry result. Some laboratories use a slightly different method, and potassium was included in some older formulas, but the sodium-based version is the version most often used in everyday practice.
For example 1, if the serum sodium is 140, the serum chloride is 102, and the serum bicarbonate is 24, the anion gap is 140 − (102 + 24) = 14. That result may fall within the normal reference range depending on the method used.
For example 2, if the serum sodium is 138, the serum chloride is 100, and the serum bicarbonate is 12, the anion gap is 138 − (100 + 12) = 26. That higher value raises concern for high anion gap metabolic acidosis and should warrant review of the full clinical picture.
Example 3: if the sodium is normal but bicarbonate is low with a normal gap, this may point toward normal anion gap metabolic acidosis. The calculator assists in identifying the pattern, but interpretation depends on the cause and associated findings.
Normal anion gap reference range and what affects it
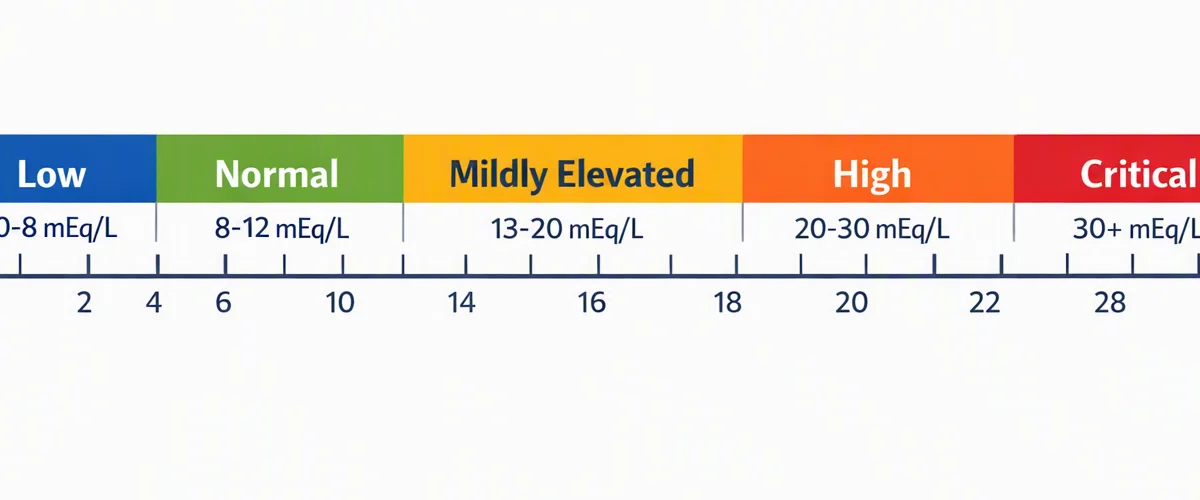
The expected range for anion gap differs by testing facility because of variations in testing methods and reporting standards. That is why the lab reference range listed on the report is more important than a single universal cutoff. A result that looks high in one lab may be within range in another.
Albumin is one of the most important factors that influences the result. Since albumin is a negative-charged protein, lower albumin levels can make the gap appear reduced than it truly is. In patients with low albumin, albumin correction may be necessary to better estimate the true gap. This is a reason a single number should not be interpreted in isolation by itself.
Other influences include alterations in measured cations, shifts in protein levels, and variations in analyzer techniques. Some medications, toxins, and uncommon blood proteins can also affect the value. For this https://pastelink.net/tu0tgte4 reason, interpreting the anion gap is not just a math problem; it is a evaluation of chemistry, context, and pattern recognition.
High anion gap compared with normal anion gap
A elevated result often suggests high anion gap metabolic acidosis, which occurs when unmeasured acids accumulate in the blood. Common causes include lactic acidosis, ketoacidosis, and kidney failure. In these situations, bicarbonate is depleted as the body counteracts excess acid, and the gap rises because the missing bicarbonate is replaced by unmeasured anions.
Lactic acidosis can occur when tissues do not get enough oxygen, when severe infection is present, or when other systemic stressors drive lactate production. Ketoacidosis is often associated with diabetes, alcohol use, or prolonged fasting. Kidney failure can reduce the body’s ability to clear acids, which also widens the gap.
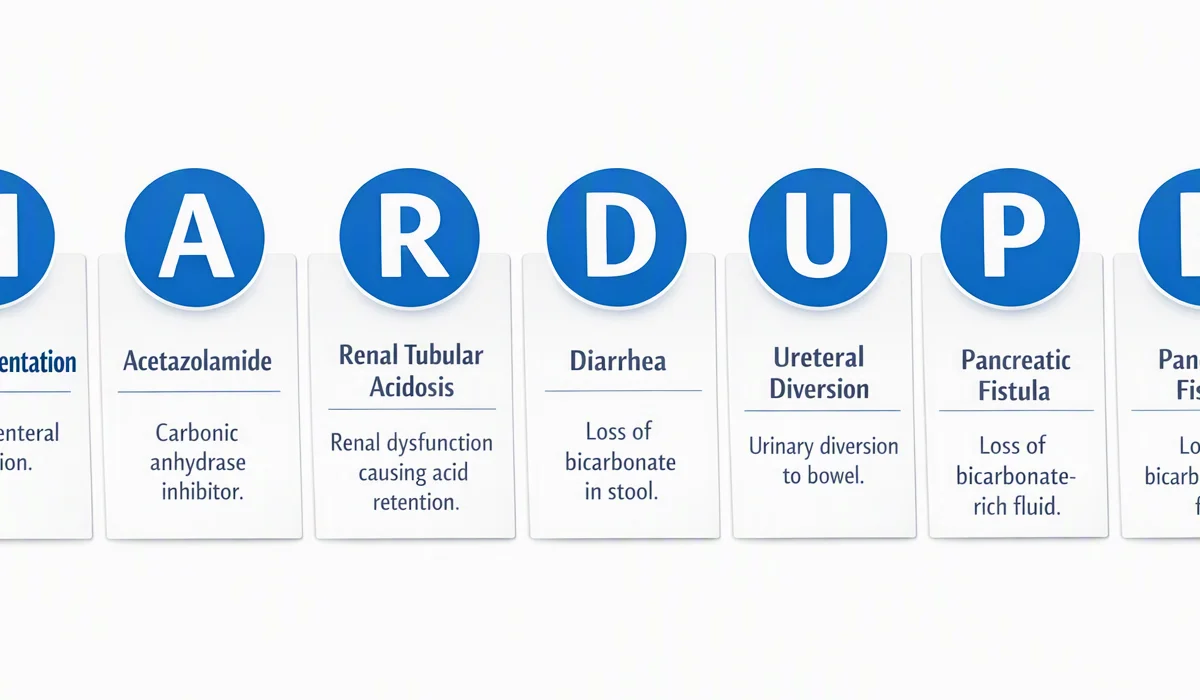
By contrast, normal anion gap metabolic acidosis usually reflects a loss of bicarbonate rather than buildup of unmeasured acid. Common mechanisms include gastrointestinal bicarbonate loss or renal tubular problems. The gap stays normal because chloride often rises to balance the loss of bicarbonate, even though the patient still has an acid-base problem.
Understanding whether the pattern is high or normal is a major step in the interpretation of the result. Both patterns can signal a serious metabolic disorder, but they point toward different underlying cause pathways and therefore different next steps.
Reduced anion gap origins and clinical meaning
A reduced anion gap is not as common than a high one, but it can still be medically important. One of the most frequent causes is hypoalbuminemia, because albumin adds substantially to the unmeasured anions in blood. When albumin is low, the gap may decrease even if there is no true acid-base abnormality.
Albumin correction is especially relevant here. If the albumin is low, a corrected calculation may indicate that the apparent low gap is mostly driven by reduced protein levels rather than a separate disorder. This avoids overcalling an abnormal result and helps identify the real issue.
Other contributors include lab artifact, elevated unmeasured positively charged proteins, and certain medications or toxins. Multiple myeloma is a classic clinical association because abnormal immunoglobulins can reduce the gap. Lithium exposure can also lower the gap because lithium is an unmeasured cation that may alter the balance of charged particles.
A low value should not be dismissed, but it should also not be overinterpreted without the full picture. The result may suggest protein changes, medication effects, or measurement issues rather than a dangerous acid-base problem. That is why review of the full chemistry report and clinical scenario is essential.
How to interpret anion gap in blood test results
Effective blood test interpretation begins with the whole electrolyte panel, not only one number. The anion gap should be viewed together with sodium, chloride, bicarbonate, kidney function, glucose, and other relevant abnormal results. A single abnormal result may matter less than a consistent pattern across several measurements.
To begin, confirm that the values came from a trusted blood chemistry panel and that the reported normal range used by the lab matches the method used by that lab. Next, look at the bicarbonate level. If bicarbonate is low, ask whether the anion gap is high, normal, or low, because that distinction can assist in narrowing the diagnosis.
Then, consider the medical context. Symptoms, recent illness, medications, fluid status, kidney function, and nutrition all are important. For example, low albumin from chronic illness can alter the interpretation, while signs of infection or poor perfusion may make lactic acidosis more likely. This is where the calculator becomes more than just a mathematical shortcut; it helps with structured clinical reasoning.
It is also important to recognize that the anion gap is a screening clue, not a final diagnosis. A result can suggest an acid-base pattern, but it does not by itself identify the exact cause. The right next step may include repeat testing, albumin correction, blood gas analysis, or additional studies depending on the scenario.
When it’s time for clinical evaluation
Any abnormal anion gap should be considered together with symptoms and the complete picture. Small shifts without symptoms may simply need follow-up and repeat testing. However, a substantial change from the expected range, especially with low bicarbonate, may indicate severe acidosis that needs urgent attention.
Symptoms like rapid breathing, confusion, severe weakness, vomiting, chest pain, dehydration, or worsening illness can suggest a more concerning problem. In these cases, emergency care may be necessary, especially if the blood chemistry shows a significant imbalance or the person is visibly unwell.
Physician review is important whenever the result is unexpected, persistent, or paired with other concerning findings. This is particularly true if there is a history of kidney disease, diabetes, toxic exposure, infection, or unexplained changes in mental status. A clinician can relate the lab pattern with symptom assessment and decide whether additional treatment or testing is needed.
Questions about anion gap blood tests
What is an anion gap calculator used for?
An anion gap calculator is used to quickly estimate the anion gap from routine blood chemistry values. It helps clinicians and patients review blood test results, identify possible acid-base disturbances, and decide whether the pattern fits a high, normal, or low gap. It is a useful diagnostic tool, but it works best when paired with the full clinical picture.
How do you calculate anion gap from blood test results?
To calculate anion gap, use the common anion gap formula: serum sodium minus the sum of serum chloride and serum bicarbonate. In other words, serum sodium − ( serum chloride + serum bicarbonate). This can be done manually or with an Anion Gap Calculator using values from a blood chemistry panel.
What does a high anion gap mean?
A elevated result often may indicate high anion gap metabolic acidosis, meaning there may be excess unmeasured acids in the blood. Frequent causes include lactic acidosis, ketoacidosis, and kidney failure. The result should be reviewed with other lab values and the patient’s clinical context.
What can cause a low anion gap?
A low anion gap is often linked to hypoalbuminemia, since low albumin reduces the number of unmeasured anions. Other causes include multiple myeloma, lithium exposure, and occasional lab-related issues. If albumin is low, albumin correction may affect the interpretation.
Should albumin be included when interpreting the anion gap?
Yes, albumin should be taken into account because it strongly affects the result. If albumin is low, the raw number may underestimate the true gap, which is why albumin correction is often useful. Including albumin improves the accuracy of blood test interpretation and helps reduce missed acid-base abnormalities.